
Neurogenic claudication
Standing and walking can provoke leg symptoms that ease with sitting or flexion.
Spinal Narrowing · Chino Hills, CA
Spinal stenosis occurs when space around the spinal cord or nerve roots becomes reduced. Some people have no symptoms; others develop pain, numbness, weakness, or limited walking tolerance that requires careful evaluation.
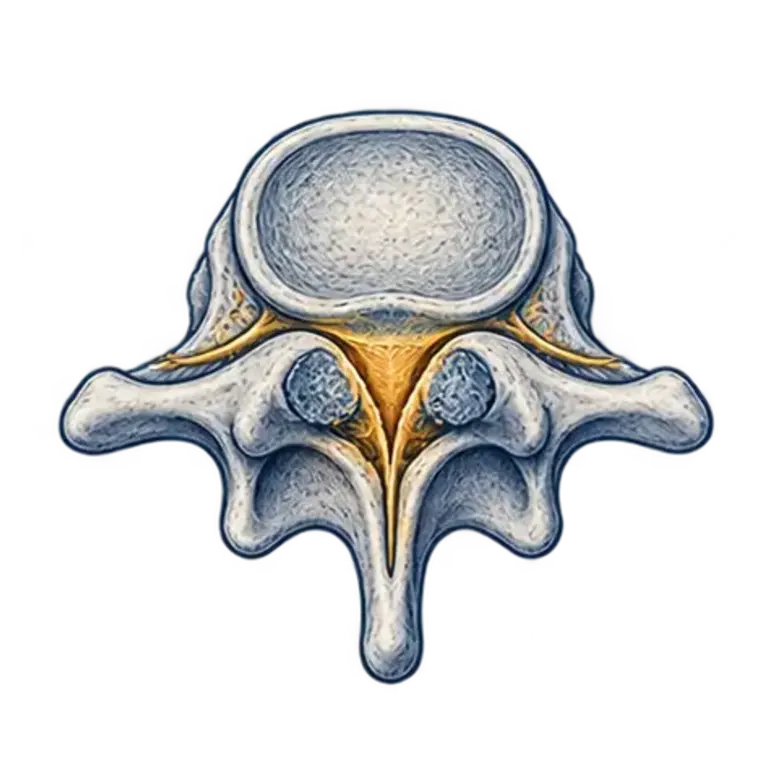
Understanding the Condition
The spinal canal and openings around nerve roots can narrow because of several changes, including thickened ligaments, enlarged facet joints, bone spurs, disc bulging, or vertebral slippage. Congenital anatomy can also leave less available space.
Lumbar stenosis may affect nerves serving the legs. Cervical stenosis can involve nerve roots or, more importantly, the spinal cord. Imaging helps describe anatomy, but symptoms, walking pattern, balance, strength, reflexes, and other examination findings guide the clinical significance.
Signs & Patterns
Symptoms differ by spinal level, severity, activity, and the structures involved. This list is educational and is not a diagnosis.
Standing and walking can provoke leg symptoms that ease with sitting or flexion.
Narrowing near an exiting nerve may create radiating pain, numbness, or weakness.
Balance loss, hand clumsiness, widespread weakness, or bowel/bladder changes require prompt medical evaluation.
Seek prompt medical evaluation for new bowel or bladder difficulty, numbness around the saddle region, rapidly increasing weakness, major trauma, fever with severe spinal pain, unexplained systemic symptoms, or sudden loss of balance or coordination.
Individual Evaluation
The purpose of the first visit is to determine the most likely pain generator, identify safety considerations, and establish whether conservative care is reasonable.
Measure walking and standing tolerance and identify positions that relieve or provoke symptoms.
Assess strength, reflexes, sensation, balance, gait, dexterity, and spinal movement as appropriate.
Review MRI, CT, or X-ray findings in relation to the clinical presentation; imaging severity alone does not determine treatment.
Distinguish neurogenic symptoms from vascular, hip, peripheral nerve, and other possible contributors.
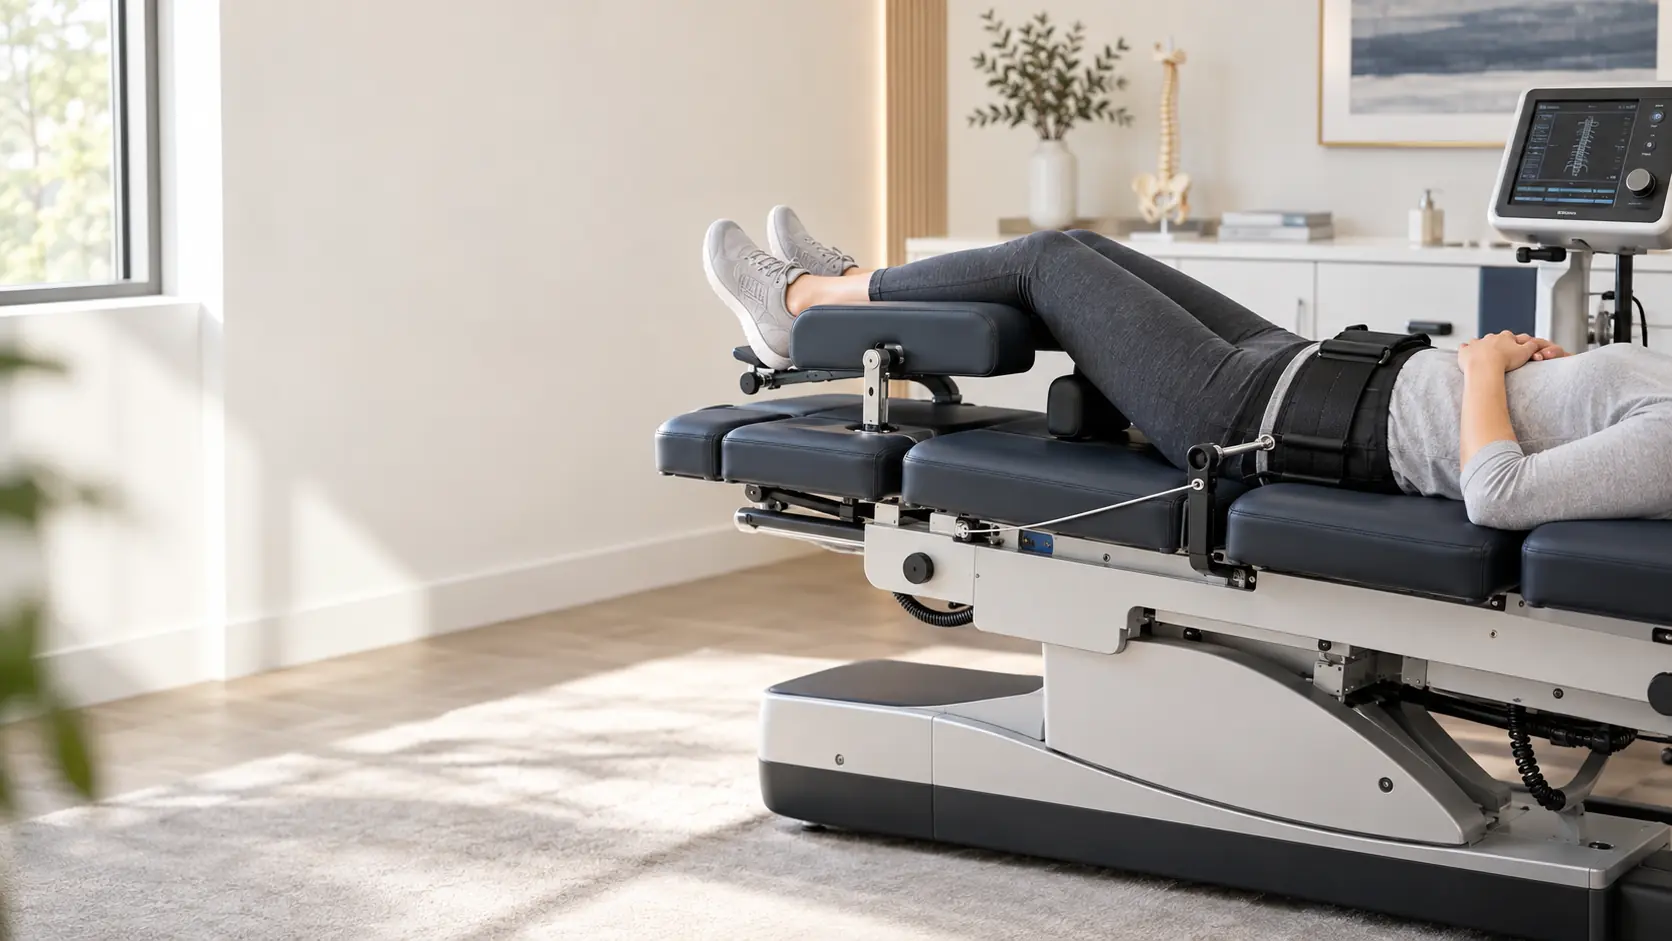
Where Decompression May Fit
Some stable lumbar stenosis presentations may be managed with conservative care. Decompression traction is considered only after the location, severity, neurological status, positional behavior, and overall health are reviewed. Cervical cord signs require medical evaluation rather than routine traction.
Research on traction shows possible short-term benefit in selected lumbar presentations, while study quality, patient selection, and long-term evidence remain limited. Individual results vary.
A Deliberate Process
Review your history, symptoms, neurological status, prior care, imaging, and goals.
If appropriate, begin with tolerable settings and clear measures of function and symptom response.
Continue, modify, combine, or refer based on meaningful progress—not a preset package.
Questions Patients Ask
No. Some people have narrowing on imaging without symptoms. Treatment decisions depend on clinical findings and function, not the image alone.
Flexion can increase available space in parts of the lumbar canal and may temporarily reduce nerve irritation in some people.
No responsible treatment should promise a cure or claim to remove bone spurs. Conservative care may focus on symptom control, function, movement tolerance, and quality of life in selected cases.
No. Cervical narrowing can involve the spinal cord, so balance, hand function, reflex, strength, and other neurological findings require particular attention.
Prompt evaluation is important for rapidly progressive weakness, new bowel or bladder difficulty, saddle numbness, major balance changes, loss of hand dexterity, severe trauma, or systemic illness.
Continue Learning
Content is educational, not a diagnosis or guarantee of outcome. Last reviewed 2026-09-14.
A personalized evaluation is the first step toward determining whether decompression—or another path—fits your case.