
Disc-dominant discomfort
Sitting, flexion, lifting, or sustained loading may be provocative in some presentations.
Disc Changes · Chino Hills, CA
“Degenerative disc disease” describes structural disc changes over time; it does not automatically mean severe damage or permanent pain. The important step is determining whether those changes match your symptoms and function.
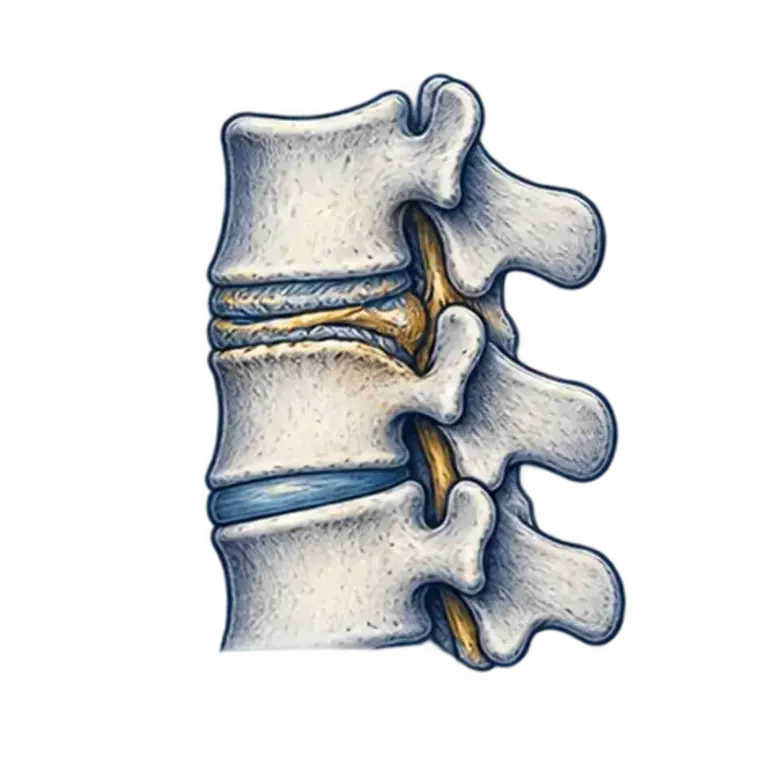
Understanding the Condition
Intervertebral discs naturally change with age and accumulated loading. They may become less hydrated, lose some height, develop small fissures, or bulge. These changes can alter how forces are shared among discs, facet joints, muscles, and ligaments.
The word “disease” can sound alarming, but degenerative findings are common and do not always produce symptoms. Care should focus on the person’s pain pattern, mobility, neurological status, activity tolerance, and goals—not on trying to make an image look young again.
Signs & Patterns
Symptoms differ by spinal level, severity, activity, and the structures involved. This list is educational and is not a diagnosis.
Sitting, flexion, lifting, or sustained loading may be provocative in some presentations.
Discs, joints, muscles, and movement habits may contribute together rather than separately.
Loss of disc height or related changes can coincide with narrowing near a nerve root.
Seek prompt medical evaluation for new bowel or bladder difficulty, numbness around the saddle region, rapidly increasing weakness, major trauma, fever with severe spinal pain, unexplained systemic symptoms, or sudden loss of balance or coordination.
Individual Evaluation
The purpose of the first visit is to determine the most likely pain generator, identify safety considerations, and establish whether conservative care is reasonable.
Clarify which positions, loads, and daily activities change symptoms.
Assess spinal and hip movement, strength, control, neurological function, and functional tolerance.
Interpret X-ray, MRI, or other imaging in context rather than treating an image by itself.
Establish measurable goals such as sitting, lifting, sleeping, walking, or returning to recreation.
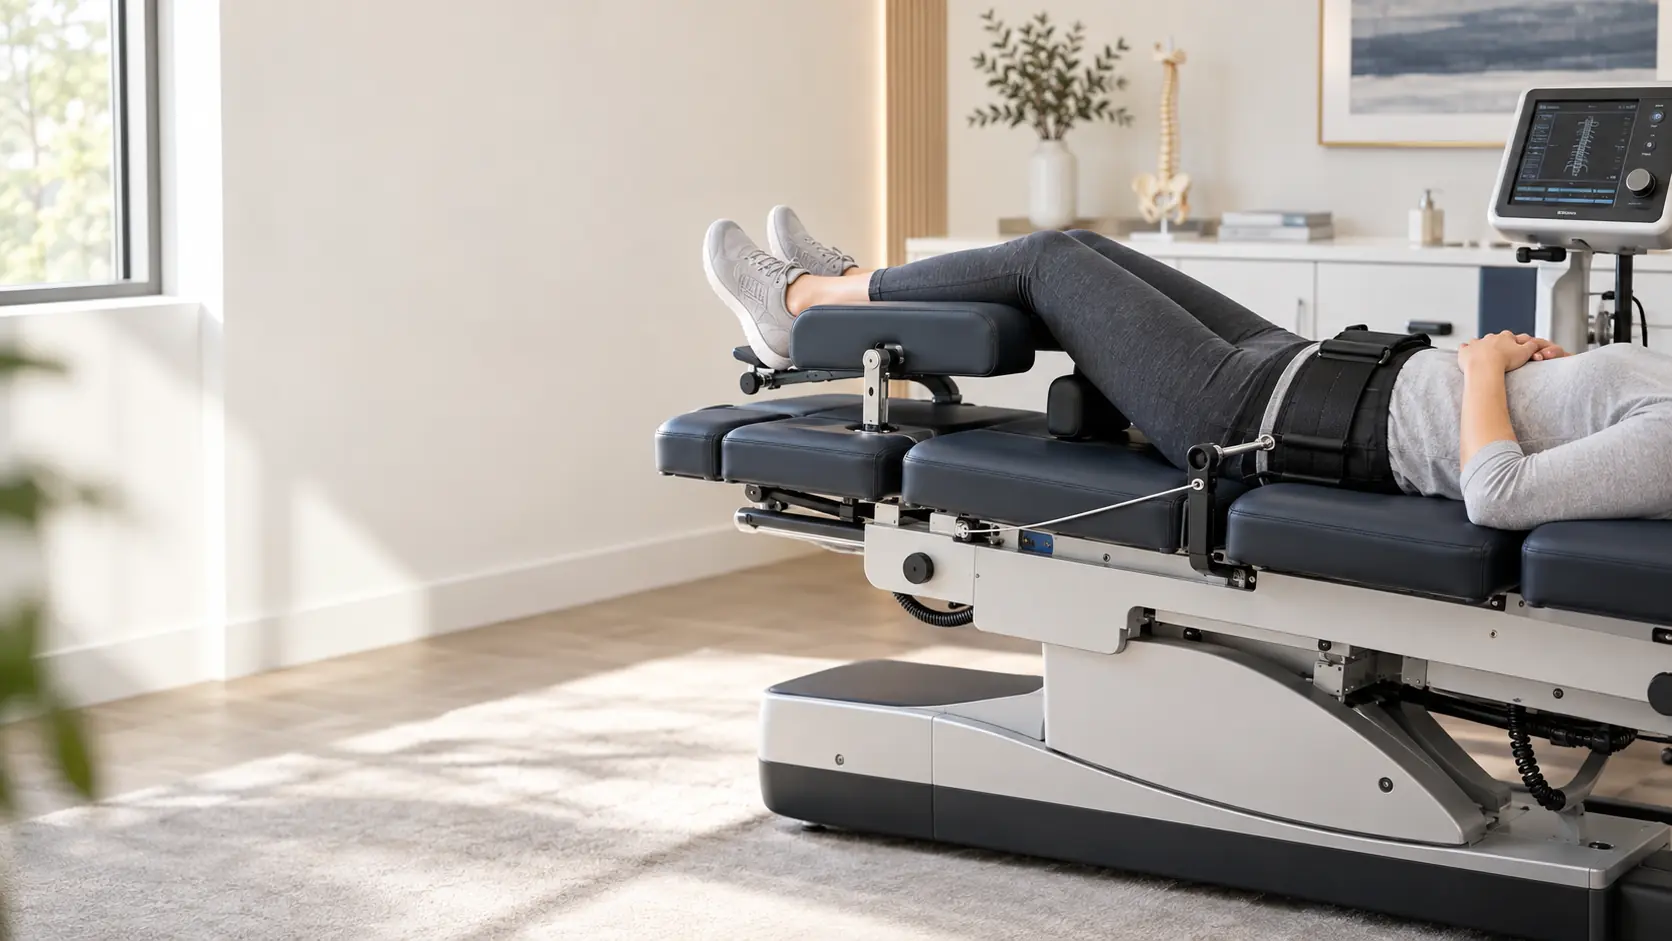
Where Decompression May Fit
Decompression may be considered when examination suggests that changing spinal loading could be useful and no contraindication is present. Because degeneration is often multifactorial, care commonly includes movement and capacity-building strategies as well.
Research on traction shows possible short-term benefit in selected lumbar presentations, while study quality, patient selection, and long-term evidence remain limited. Individual results vary.
A Deliberate Process
Review your history, symptoms, neurological status, prior care, imaging, and goals.
If appropriate, begin with tolerable settings and clear measures of function and symptom response.
Continue, modify, combine, or refer based on meaningful progress—not a preset package.
Questions Patients Ask
It describes age- and load-related disc changes. The amount seen on imaging does not reliably determine how much pain or disability a person will have.
Conservative care is aimed at improving symptoms, movement, capacity, and function—not promising to restore a disc to a younger appearance.
No. The symptom pattern, neurological findings, stability, bone health, medical history, and other factors must be screened first.
Mechanical sensitivity, activity level, sleep, stress, recovery, inflammation, and other structures can influence symptoms even when imaging does not change.
Useful progress can include better sitting or walking tolerance, fewer symptom flares, improved sleep, easier movement, or a return to valued activities.
Continue Learning
Content is educational, not a diagnosis or guarantee of outcome. Last reviewed 2026-09-14.
A personalized evaluation is the first step toward determining whether decompression—or another path—fits your case.